Dermatophytose
Tinea infections
Revu par Dr Philippa Vincent, MRCGPDernière mise à jour par Dr Doug McKechnie, MRCGPDernière mise à jour 27 fév 2025
Respecte les directives éditoriales
- TéléchargerTélécharger
- Partager
- Language
- Discussion
- Ask Patient
- Version audio
- Ajouter aux sources préférées sur Google
Professionnels de la santé
Les articles de référence professionnelle sont conçus pour être utilisés par les professionnels de la santé. Ils sont rédigés par des médecins britanniques et basés sur des preuves de recherche, des directives britanniques et européennes. Vous pouvez trouver le Infections fongiques article plus utile, ou l'un de nos autres articles de santé.
Contexte1
Dermatophytosis (tinea) infections are fungal infections caused by dermatophytes - a group of fungi that invade and grow in dead keratin. Several species commonly invade human keratin and these belong to the Epidermophyton, Microsporum et Trichophyton genera. They tend to grow outwards on skin, producing a ring-like pattern - hence the term 'ringworm'. They are very common and affect different parts of the body. They can usually be successfully treated but success depends on the site of infection and on compliance with treatment.
Voir le séparé Tinea capitis, Infections fongiques des ongles, Pityriasis versicolor et Candidose articles.
Physiopathologie23
Infection is limited to the dead layers of skin but encouraged by a damp and warm local environment.
The infection can be transmitted to humans by anthropophilic (between people), geophilic (from soil) and zoophilic (from animals) spread.
The most common organisms are:
Trichophytons rubrum, Trichophytons tonsurans, Trichophytons interdigitale et Trichophytons mentagrophytes.
Microsporum canis.
Epidermophyton floccosum.
Clinical classification is according to site:
Scalp - tinea capitis.
Feet - tinea pedis.
Hands - tinea manuum.
Nail - tinea unguium (or onychomycosis).
Beard area - tinea barbae.
Groin - tinea cruris.
Body including trunk and arms - tinea corporis.
Épidémiologie
Infection is very common all over the world. Some types are more common than others, with tinea pedis being most common in adults and tinea capitis the most common in children. Onychomycosis is also extremely common.
Présentation2
Historique
Itching, rash and nail discolouration are the most common symptoms of tinea infection.
Hair loss occurs with tinea capitis (mainly a disease of children).
Complications such as secondary infection (cellulitis and impetigo) can lead to symptoms.
It is common in people who play contact sports.
It occurs in immunocompromised patients.
Examen
Tinea pedis:4
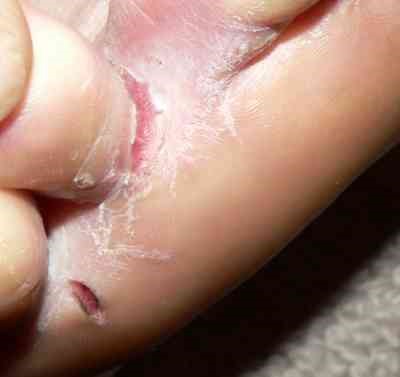
It particularly affects the web of the toe where skin may be macerated and erythematous.
It commonly affects the plantar surface of the foot. Erythema, vesicles and pustules can occur.
Tinea pedis - entre les orteils
It can cause hair loss with broken hairs at the surface (as distinct from alopecia areata).
Clinical appearance is variable, including scaly, crusting, pustules and/or black dot alopecia.
Tinea unguium (onychomycosis):6
Onycholysis or separation of the nail from the nail bed commonly occurs.
Nail dystrophy with thickening and discolouration of the nail develops.
Tinea corporis:7
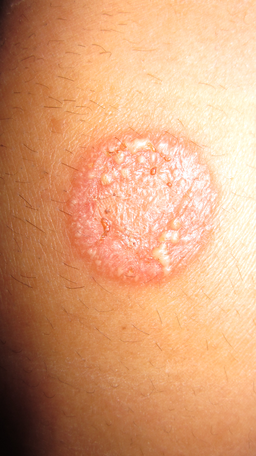
The skin lesions have annular scaly plaques with raised edges.
There may be vesicles and pustules.
Typically lesions are on exposed skin of the trunk, arms and legs (see 'Differential diagnosis', below).
More unusually the lesions can appear as overlapping concentric circles (tinea imbricate) or even herpetiform subcorneal vesicles or pustules (bullous tinea corporis).
Tinea corporis
Tinea manuum:
Usually with tinea pedis.
Typically just affects one hand.
Scaling and redness are prominent.
Incorrect diagnosis and use of steroid may eventually exacerbate the infection.
Tinea cruris:8
Usually occurs in men.
Often tolerated for some time before presentation.
Typically erythematous with central clearing and raised edge.
Tinea barbae:9
Affects the beard area.
Redness, scaling and pustules are common.
Diagnostic différentiel7
Other annular rashes are often confused with tinea infections. Eczéma et psoriasis are commonly confused with tinea. Pityriasis versicolor occurs all over the trunk while candida occurs as a flexural rash at extremes of age or in the immunocompromised, those with diabetes or patients on antibiotics.
Treatment with topical steroids often causes confusion, making tinea less scaly and more erythematous. Steroid use also makes the 'active' edge and the inactive centre less distinct (tinea incognito). Clinically the diagnosis can be difficult but, if it is a possibility, take scrapings for mycology. Other fungal infections look nothing like tinea. Other conditions to consider include:
Intertrigo.
Erythrasma.
Enquêtes10
Microscopy of skin and nail specimens may reveal hyphae and spores.
Fungal culture can identify the species but is not always reliable and it can take six weeks to obtain results.
Ultraviolet light (Wood's light) is useful for tinea capitis especially. Fluorescence is produced by the fungus. Fluorescence is not seen with tinea corporis or tinea cruris.
Rarely, a biopsy may be needed if the case is atypical or not responding to treatment.
Maladies associées
Diabetes, immunocompromised states, atopy and Syndrome de Cushing have all been associated with fungal infections.
Gestion45610
Offer advice on hygiene measures:
Keep affected skin cool and dry.
Wear cotton, absorbent clothing.
Avoid scratching affected skin.
After washing, dry thoroughly.
Do not share towels, and wash frequently, to reduce the risk of transmission.
Cover feet in communal bathing pools, changing areas and gymnasiums if feet are affected.
Continue school and sporting activities.
Voir le séparé Médicaments antifongiques article.
Topical agents containing a corticosteroid are not usually necessary. They may be used if there is a lot of skin inflammation. They should be used for a week only.
Referral may be needed if diagnosis is in doubt.
Complications
Secondary bacterial infection may occur. Hair loss is a complication of tinea capitis. Pain and difficulty with shoes can result from onychomycosis.
A dermatophytid (id) reaction may occur, especially after initiation of systemic antifungal treatment. This is thought to be a type IV hypersensitivity response, and causes a widespread pruritic rash, with papules, maculopapules, papulovesicles, or pustules at sites distinct from that of the original dermatophyte infection.11
Scarring is uncommon but more likely in people with pigmented skin. Scarring usually fades with time. Skin protection such as using a moisturiser cream and sunscreen can be helpful. Extensive or severe scarring may need further treatment, such as using laser therapy.
Pronostic
Excellent with good compliance and subsequent precautions to avoid repeat infection.
Prévention
Good skin hygiene.
Good nail hygiene.
Avoiding prolonged wetting or dampness of the skin and feet.
Avoiding trainers, which can retain sweat and promote a warm, moist environment.
Treatment of tinea pedis - helps prevent onychomycosis.6
Wearing clean, loose-fitting underwear.
Mises à jour exclusives pour les professionnels de la santé
Restez informé des dernières mises à jour cliniques, des perspectives professionnelles et des conseils fondés sur des preuves. La newsletter Patient Pro sélectionne des contenus essentiels pour les professionnels de santé—livrés directement dans votre boîte de réception.
En vous abonnant, vous acceptez notre Politique de confidentialité. Vous pouvez vous désabonner à tout moment. Nous ne vendons jamais vos données.
Lectures complémentaires et références
- Dermatophytide reactions; DermNet NZ
- Sahoo AK, Mahajan R; Management of tinea corporis, tinea cruris, and tinea pedis: A comprehensive review. Indian Dermatol Online J. 2016 Mar-Apr;7(2):77-86. doi: 10.4103/2229-5178.178099.
- Ely JW, Rosenfeld S, Seabury Stone M; Diagnosis and management of tinea infections. Am Fam Physician. 2014 Nov 15;90(10):702-10.
- Martinez DA, Oliver BG, Graser Y, et al; Comparative genome analysis of Trichophyton rubrum and related dermatophytes reveals candidate genes involved in infection. MBio. 2012 Sep 4;3(5):e00259-12. doi: 10.1128/mBio.00259-12. Print 2012.
- The Cutaneous Mycoses; Mycology Online
- Hainer BL; Dermatophyte infections. Am Fam Physician. 2003 Jan 1;67(1):101-8.
- Infection fongique de la peau - pied; NICE CKS, juin 2023 (accès réservé au Royaume-Uni)
- Infection fongique de la peau - cuir chevelu; NICE CKS, juin 2023 (accès réservé au Royaume-Uni)
- Infection fongique des ongles; NICE CKS, août 2023 (accès réservé au Royaume-Uni)
- Infection fongique de la peau - corps et aine; NICE CKS, juillet 2023 (accès réservé au Royaume-Uni)
- Tinea Cruris; DermNet NZ
- Tinea barbae; DermNet NZ
- Infections fongiques de la peau et des ongles : Diagnostic et investigation en laboratoire - Guide de référence rapide pour les soins primaires; GOV.UK, 2017
- Leung AK, Lam JM, Leong KF, et al; Tinea corporis: an updated review. Drugs Context. 2020 Jul 20;9:2020-5-6. doi: 10.7573/dic.2020-5-6. eCollection 2020.
À propos de l'auteurVoir la biographie complète
Mis à jour par

Dr Doug McKechnie, MRCGP
Rédacteur Médical
MA, MBBS, MSc, DRCOG, MRCP(UK), MRCGP(2021), FHEA
Le Dr Doug McKechnie est un médecin généraliste du NHS travaillant à Londres. Il travaille à plein temps en clinique et est également le chef adjoint du module de Pratique Clinique et Professionnelle à l'École de Médecine de l'University College London.
À propos du critiqueVoir la biographie complète

Dr Philippa Vincent, MRCGP
Médecin généraliste, Auteur médical
MB BS, Bsc, MRCGP (2000), DCH, DFSRH, DRCOG
Dr Philippa Vincent est un médecin généraliste du NHS travaillant dans le nord de Londres.
Historique de l'article
Article également disponible en Anglais, Allemand, Espagnol, Français, Italien, Portugais, Hindi, Hébreu, Arabe, and Suédois.
Prochaine révision prévue : 26 févr. 2028
27 fév 2025 | Dernière version
Accès simple à des traitements fiables et à des services de santé en ligne.
Common conditions
Get help with common conditions through the NHS, without a GP appointment.





Plus en dermatologie
- Kératose actinique
- Nævus bleu
- Larva migrans cutanée
- Lupus érythémateux discoïde
- Ecthyma
- Dermatose neutrophilique fébrile
- Folliculite
- Herpès génital simplex
- Purpura de Henoch-Schönlein
- Hirsutisme
- Kératose pilaire
- Lichen simplex
- Masse
- Melasma
- Pityriasis versicolor
- Maladie des ongles psoriasiques
- Scarlatine
- Hippocratisme digital
- Urticaire
- Syndrome des ongles jaunes