
Angine de poitrine
Revu par Dr Toni Hazell, FRCGPDernière mise à jour par Dr Hayley Willacy, FRCGP Dernière mise à jour 30 janv. 2023
Respecte les directives éditoriales
- TéléchargerTélécharger
- Partager
- Language
- Discussion
- Version audio
- Ajouter aux sources préférées sur Google
Dans cette série :Angine microvasculaireSpasme de l'artère coronaire
Angina is a pain that comes from the heart. It is usually caused by narrowing of the heart's blood vessels - the (coronary) arteries. Usual treatment includes a statine medicine to lower your cholesterol level, low-dose aspirin to help prevent a heart attack, and a bêta-bloquant medicine to help protect the heart and to prevent angina pains. An inhibiteur de l'enzyme de conversion de l'angiotensine (ECA) medicine is advised in some cases. Sometimes angioplasty or surgery are options to widen, or to bypass, narrowed arteries.
En un coup d'œil
Angina is chest pain that comes from the heart.
It usually occurs when your heart needs more blood than narrowed arteries can supply.
Les symptômes incluent une sensation d'oppression dans la poitrine, qui peut s'étendre aux bras, à la mâchoire ou à l'estomac.
La douleur s'aggrave généralement avec l'effort et s'atténue au repos, généralement en moins de 10 minutes.
Si la douleur dure plus de 10 minutes, ou est plus sévère, appelez immédiatement une ambulance.
What is angina?
Angina is a pain that comes from the heart. Each year about 20,000 people in the UK develop angina for the first time. It is more common in people over the age of 50 years. It is also more common in men than in women. Sometimes it occurs in younger people.
This leaflet is about the common type of angina which is caused by narrowing in the coronary arteries of the heart. Sometimes angina can be caused by uncommon disorders of the heart valves or heart muscle.
What causes angina?
Cœur avec athérome
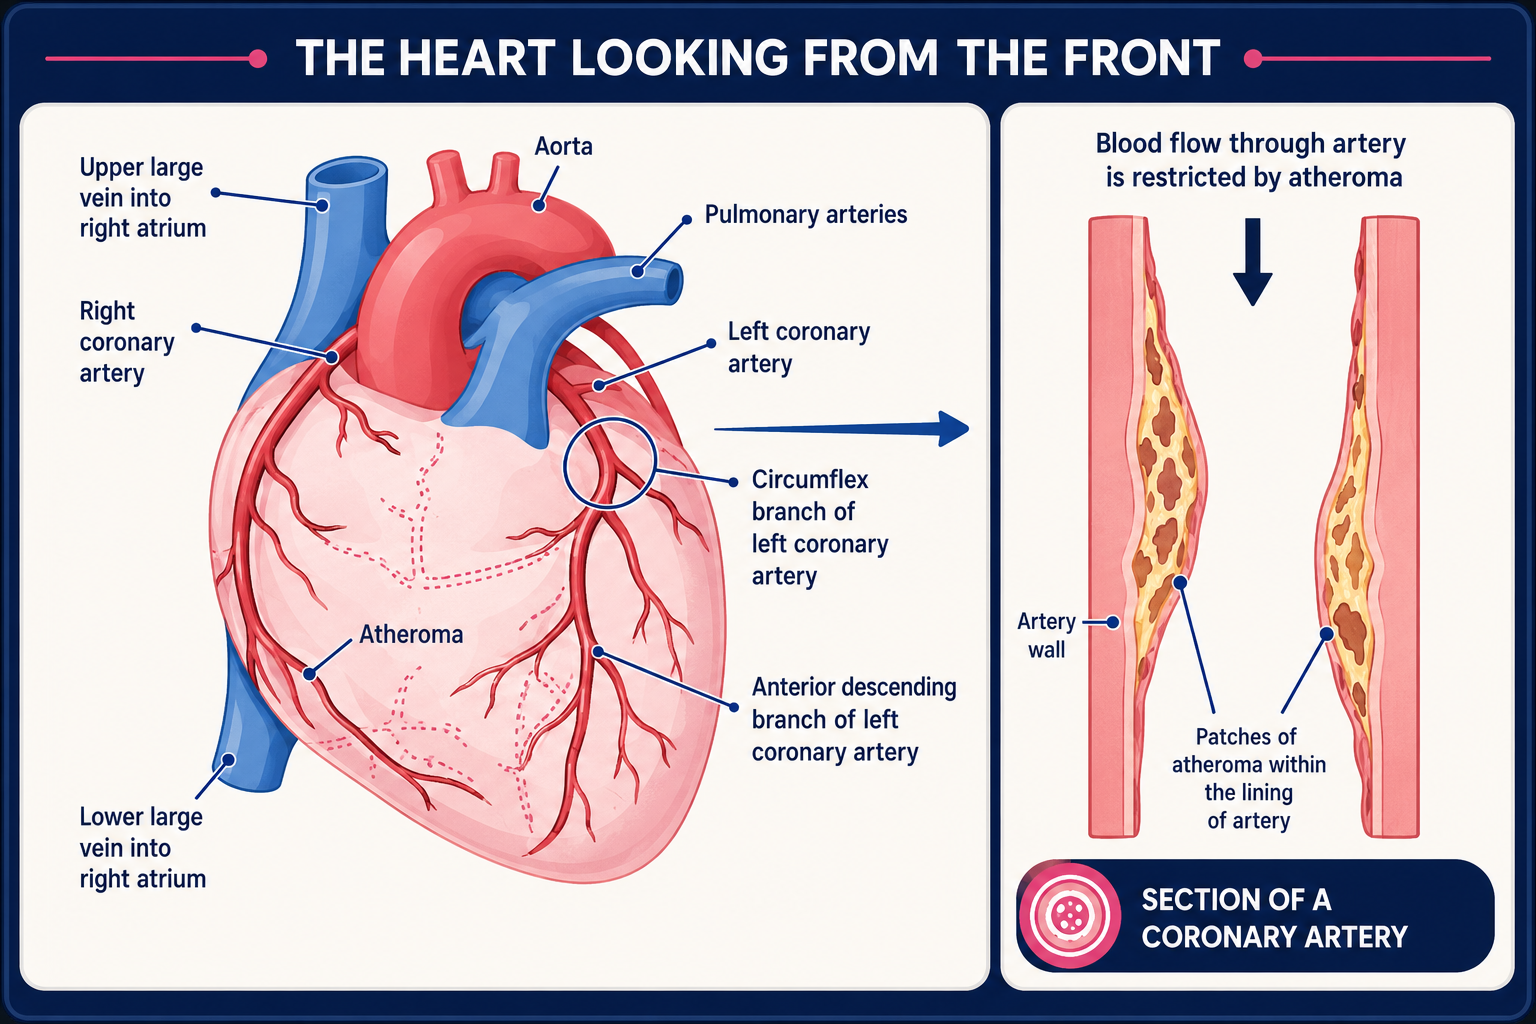
If you have angina, one or more of your heart (coronary) arteries are usually narrowed. This causes a reduced blood supply to a part, or parts, of your heart muscle.
The blood supply may be good enough when you are resting. When your heart works harder (when you walk fast or climb stairs and your heart rate increases) your heart muscle needs more blood and oxygen. If the extra blood that your heart needs cannot get past the narrowed coronary arteries, the heart responds with pain.
The narrowing of the arteries is caused by atheroma. See the separate leaflet called High Cholesterol for more information about atheroma.
Angina can also be caused by:
Spasm of the coronary arteries. Read more about coronary artery spasm.
Other problems with the blood supply to the heart. Read more about cardiac syndrome X (microvascular angina).
Angina symptoms
Typical and common angina symptoms
Pain, ache, discomfort or tightness that you feel across the front of the chest.
The pain is usually worse when you exert yourself. For example, when you walk up a hill or against a strong, cold wind.
You may also, or just, feel the pain in your arms, jaw, neck or stomach.
An angina pain does not usually last long. It will usually ease within 10 minutes when you rest.
If you take some trinitrate de glycéryle (GTN) it should go within 1-2 minutes (see 'Glyceryl trinitrate' section, below).
Angina pain may also be triggered by other causes of a faster heart rate - for example, when you have a vivid dream or an argument. The pains also tend to develop more easily after meals.
See also the separate leaflet called Chest Pain.
Less typical symptoms that sometimes occur
Some people have non-typical pains - for example, pains that develop when bending or eating.
If the symptoms are not typical then it is sometimes difficult to tell the difference between angina and other causes of chest pain, such as a pulled muscle in the chest or heartburn.
Some people with angina also become breathless when they exert themselves. Occasionally, this is the only symptom and there is no pain.
What tests will I have for angina?
If you have suspected angina, tests are usually advised:
Analyses de sang to check for anaemia, thyroid problems, kidney problems, a high blood sugar (glucose) level and a high cholesterol level, as these may be linked with angina.
Un tracé cardiaque (électrocardiogramme, ou ECG). This can be useful. However, a routine ECG may be normal if you have angina. In fact, more than half of people with angina have a normal resting ECG.
How do doctors know that I have angina?
In many cases doctors can make the diagnosis based on the typical symptoms. No further tests may then be necessary. Tests are advised in some cases when the diagnosis is not clear, or sometimes to assess the severity of the condition. The tests that you have will depend on what is available locally and whether the test is suitable for you. One or more of these may be advised:
An ultrasound scan of the heart (echocardiogram, or 'echo').
Un examen d'imagerie par résonance magnétique (IRM) can also show how your heart works under stress.
Test de tolérance à l'exercice has been used for many years to diagnose and assess the severity of angina. However, this test is done less often these days due to more the more modern tests (listed above) becoming available. Current UK guidelines do not recommend using exercise testing to make the initial diagnosis of angina.
What can I do to help with angina?
Certain risk factors increase the risk of more fatty patches or plaques (atheroma) forming, which can make angina worse. Voir la brochure séparée intitulée Maladie cardiovasculaire (Athérome) pour plus de détails.
Briefly, risk factors that can be modified and may help to prevent angina from becoming worse include:
Tabagisme. If you smoke, you should make every effort to stop.
Hypertension artérielle. Your blood pressure should be checked regularly, at least once a year, if you have angina. If it is high, it can be treated.
Si vous êtes en surpoids, losing some weight is advised. Perdre du poids réduira la charge de travail de votre cœur et aidera également à abaisser votre tension artérielle.
Hypercholestérolémie. This should be treated if it is high.
Inactivité. Vous devriez viser à faire une activité physique modérée on most days of the week for at least 30 minutes. For example, brisk walking, swimming, cycling, dancing, gardening, etc. (Occasionally, angina is due to a heart valve problem where physical activity may not be so good. Ask your doctor to confirm that you can undertake regular physical activity.)
Régime alimentaire. Vous devriez viser à manger un régime sain. A healthy diet means:
At least five portions (and ideally 7-9 portions) of a variety of fruit and vegetables per day.
You should not eat much fatty food such as fatty meats, cheeses, full-cream milk, fried food, butter, etc. Ideally you should use low-fat, mono-unsaturated or polyunsaturated spreads.
Try to include 2-3 portions of fish per week, at least one of which should be oily (such as herring, mackerel, sardines, kippers, salmon, or frais tuna).
If you eat red meat, it is best to eat lean red meat, or eat poultry such as chicken.
Si vous faites frire des aliments, choisissez une huile végétale comme l’huile de tournesol, de colza ou d’olive.
Try not to add salt to food. Limit foods which are salty.
Alcohol definitely has a harmful effect on heart health when consumed above the recommended guideline amounts - ie 14 units per week maximum with at least two completely alcohol-free days in the week. However when alcohol is consumed at a lower level than that, the effect on risks is less clear.
Angina treatment
Les principaux objectifs du traitement sont :
To prevent angina pains as much as possible and to ease pain quickly if it occurs.
To limit further deposits of fatty patches or plaques (atheroma) as much as possible. This prevents or delays the condition from worsening.
To reduce the risk of having a heart attack (myocardial infarction).
Treatments that are advised in most cases
In addition to the lifestyle factors listed above, the treatments for angina include:
Glyceryl trinitrate (GTN) to relieve an angina episode.
Aspirin or another antiplatelet medicineto reduce the risk of blood clots.
A beta-blocker medicine to prevent the heart beating too fast.
Other treatments that may be advised
Other medicines to prevent angina pains
A beta-blocker may be sufficient to prevent angina pains but other medicines are available if required. They fall into three main groups:
Bloqueurs des canaux calciques (par exemple, amlodipine).
Nitrate medicines (par exemple, isosorbide mononitrate).
Potassium-channel activators (par exemple, nicorandil).
Non-medicine treatments
Angioplastie coronarienne ou coronary artery bypass graft (CABG) surgery may be offered if:
You have pains not controlled by medicines; ou
The site and severity of the atheroma deposits are particularly suited to one of these treatments. In some cases this may even be if you have few or no pains, as the overall outlook may be improved in certain circumstances.
Common worries about angina
Straining the heart by exertion
This is a common worry. On the contrary, more physical activity is usually advised. You will normally be encouraged to exercise regularly. Physical activity helps to make the heart fitter and improves the blood supply to the heart muscle.
Sexe
Some people with angina worry that the physical effort of having sex will damage the heart. This is wrong and you do not need to stop having sex. If sex does bring on an angina pain, it may be helpful to take some GTN beforehand.
Conduire et voler
There is usually no restriction for driving your own car unless pains occur at rest, with emotion or while driving. But, you must inform your insurance company if you have angina. People with PCV or LGV licences, who have angina, must stop driving and, in the UK, contact the DVLA.
As regards flying, in general, if you can climb 12 stairs and walk 100 metres on the level without pain or becoming very breathless, you are fit to fly as a passenger. People with frequent angina pains or unstable angina should avoid flying. Please note that your GP is not able to sign a form stating that you are fit to fly. This must be assessed by a doctor who has been specifically trained for this task.
Other points about angina
Stable angina and unstable angina
In most cases, angina pains come on with a certain amount of exertion and you can predict the level of exertion that triggers a pain. This situation is called stable angina. More than a million people in the UK have stable angina. It is common to have stable angina for many years and, with treatment, most pains can be prevented. Over months or years the pains may come on with a lesser amount of exertion if the condition gradually becomes worse.
If the pattern of your pain changes fairly suddenly and the pains develop after minimal exertion, or while you are resting, this is called unstable angina. This is an emergency and needs immediate medical care.
Prolonged pain
If you have a pain that lasts longer than 10 minutes, does not respond to your GTN or is different or more severe than usual, call an ambulance immediately. It may be unstable angina or a crise cardiaque and immediate medical care is needed.
Immunisation
People with angina should have the pneumococcal immunisation et le annual flu immunisation.
Sélections des patients pour Maladies cardiaques

Santé cardiaque et vaisseaux sanguins
Sténose aortique
La valve aortique est une valve cardiaque située entre le ventricule gauche et l'aorte. En cas de sténose aortique, lorsque la valve aortique s'ouvre pour laisser passer le sang, elle ne s'ouvre pas aussi largement qu'à la normale. L'ouverture entre le ventricule gauche et l'aorte est donc rétrécie (sténosée). La quantité de sang pouvant passer du ventricule gauche à l'aorte est donc réduite. Plus la valve est rétrécie, moins il y a de sang qui peut passer, et plus les symptômes sont importants. Dans certains cas, la sténose aortique survient en même temps qu'une régurgitation aortique.
par Dr Philippa Vincent, MRCGP

Santé cardiaque et vaisseaux sanguins
Sténose mitrale
La sténose mitrale signifie que lorsque la valve mitrale s'ouvre, elle ne s'ouvre pas complètement. L'ouverture est donc plus étroite que la normale (sténosée).
par Dr Colin Tidy, MRCGP
Questions fréquemment posées
L'angine peut-elle durer plusieurs jours ?
Non, une douleur d'angine typique ne dure généralement pas longtemps. Elle s'atténuera généralement en 10 minutes lorsque vous vous reposez. Si la douleur dure plus de 10 minutes, ne répond pas à votre médicament GTN, ou semble différente ou plus sévère que d'habitude, vous devriez appeler une ambulance immédiatement.
Combien de temps peut-on vivre avec des artères bouchées ?
De nombreuses personnes vivent avec des artères coronaires rétrécies pendant de nombreuses années, surtout avec un traitement approprié et des changements de mode de vie. Le but du traitement de l'angine de poitrine est de prévenir l'aggravation de la condition, de réduire le risque de crise cardiaque et de gérer efficacement les douleurs.
Pourquoi les douleurs d'angine ont-elles tendance à se développer plus facilement après les repas ?
Les douleurs d'angine peuvent être déclenchées plus facilement après les repas car la digestion augmente temporairement la charge de travail de votre cœur en pompant plus de sang vers le système digestif. Si les artères de votre cœur sont rétrécies, cette demande supplémentaire peut entraîner des douleurs.
Quelle est la différence entre l'angine stable et l'angine instable ?
L'angine stable se réfère à des douleurs qui surviennent de manière prévisible avec un certain niveau d'effort. Avec l'angine stable, vous pouvez généralement anticiper quelles activités pourraient déclencher la douleur. L'angine instable, cependant, est une urgence où le schéma de la douleur change soudainement, se développant avec un effort minimal ou même au repos. Cela nécessite une attention médicale immédiate.
Dois-je arrêter de conduire si j'ai de l'angine de poitrine ?
En général, vous n'avez généralement pas besoin de restreindre la conduite de votre propre voiture, sauf si vous ressentez des douleurs au repos, avec émotion ou en conduisant. Cependant, vous devez informer votre compagnie d'assurance si vous avez de l'angine de poitrine. Pour les personnes titulaires de permis PCV ou LGV, si vous avez de l'angine de poitrine, vous devez arrêter de conduire et contacter la DVLA.
Lectures complémentaires et références
- Évaluer l'aptitude à conduire : guide pour les professionnels de santé; Agence des licences de conducteur et de véhicule
- Gestion de l'angine stable; Réseau Écossais de Directives Intercollégiales - SIGN (Avril 2018)
- Saraste A, Knuuti J; ESC 2019 guidelines for the diagnosis and management of chronic coronary syndromes : Recommendations for cardiovascular imaging. Herz. 2020 Aug;45(5):409-420. doi: 10.1007/s00059-020-04935-x.
- Angine de poitrine; NICE CKS, octobre 2022 (accès réservé au Royaume-Uni)
- Mahtani AU, Padda IS, Johal GS; Cardiac Syndrome X.
- Hoek AG, van Oort S, Mukamal KJ, et al; Consommation d'alcool et risque de maladies cardiovasculaires : contextualiser les nouvelles données. Curr Atheroscler Rep. 2022 Jan;24(1):51-59. doi: 10.1007/s11883-022-00992-1. Epub 2022 Feb 7.
À propos de l'auteurVoir la biographie complète
Mis à jour par

Dr Hayley Willacy, FRCGP
Médecin généraliste, Auteur médical
MBChB (1992), DRCOG, DFFP, MRCOG (Part 1) MRCGP (2007), DFSRH (2013), MSc - medical education (2020)
Le Dr Hayley Willacy était médecin généraliste au NHS travaillant dans le nord-ouest de l'Angleterre, qui a pris sa retraite de la pratique clinique en 2022 après 30 ans.
À propos du critiqueVoir la biographie complète

Dr Toni Hazell, FRCGP
MBBS, BSc, FRCGP, DFSRH, Dip GU med, DRCOG, DCH (London, UK, 2000)
Le Dr Toni Hazell a obtenu son diplôme de l'École de médecine de l'hôpital St. Mary et a effectué son VTS à l'hôpital Northwick Park.
Historique de l'article
Article également disponible en Anglais, Allemand, Espagnol, Français, Italien, Portugais, Hindi, Hébreu, Arabe, and Suédois.
Prochaine révision prévue : 29 janv. 2028
30 janv. 2023 | Dernière version
Participez à la conversation
Partagez vos pensées ou expériences avec les autres dans notre communautés de patients.

Demandez, partagez, connectez-vous.
Parcourez les discussions, posez des questions et partagez vos expériences sur des centaines de sujets de santé.

Vous ne vous sentez pas bien ?
Évaluez vos symptômes en ligne gratuitement
Inscrivez-vous à la newsletter Patient
Votre dose hebdomadaire de conseils de santé clairs et fiables - rédigés pour vous aider à vous sentir informé, confiant et maître de la situation.
En vous abonnant, vous acceptez notre Politique de confidentialité. Vous pouvez vous désabonner à tout moment. Nous ne vendons jamais vos données.